
Local LLM for GP Practices: A Model in the Surgery, Managed
A practice manager should never have to think about which language model the office is running. They should get complaint responses drafted, policies findable and reports assembled, with nothing leaving the surgery. The model is ours to choose and keep running.
£500 per month for the software and the hardware rental. You rent the machine — you don’t buy it.
A local LLM for GP practices is a language model running on a machine inside the surgery rather than a provider’s cloud, chosen for the practice’s policies, complaint responses, PCN reporting and patient letters. It reads administrative documents only, is not connected to the clinical system, and is installed, kept current and supported by us.
Find out which model suits the job
A short call with the practice manager or a partner. Bring your DSPT lead; we will walk through where the model runs and what it sees.
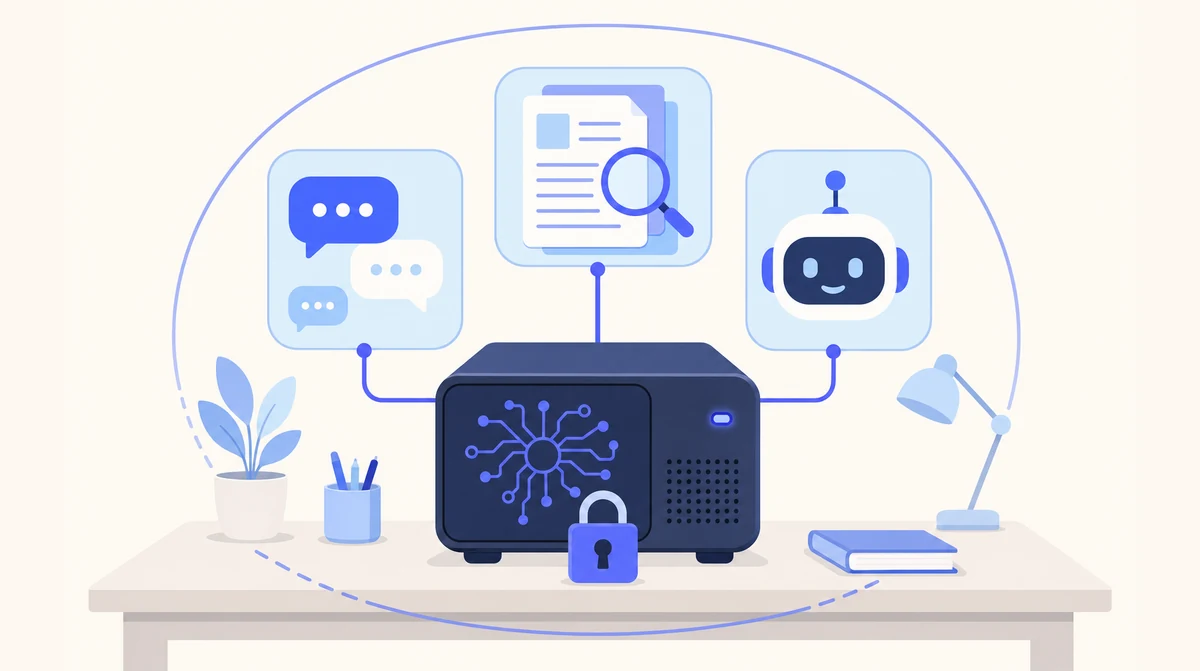
One machine in the practice office, an open-weight model chosen for practice paperwork, and the chat and document tools around it. Nothing leaves the surgery.
Cloud Agents for the Phone, Local AI for Practice Documents
Appointment calls and the admin inbox suit a hosted agent; practice policies, complaints correspondence and hospital letters suit a machine inside the surgery. Many practices run both.
- ☁ Cloud-based AI Receptionist
- ☁ Cloud-based Email Manager
- ☁ Cloud-based Leads Outreach
- 🏢 On-premise Local AI
Do It Yourself, or Have It Done
Running a local LLM is not hard for an afternoon. Running one for GP practices, every working day, with backups and someone to ring, is a different job.
| DIY on a spare machine | Cloud LLM subscription | Managed local LLM in the surgery (ours) | |
|---|---|---|---|
| Where prompts and files go | Your machine | The provider’s servers | Your machine |
| Choosing local LLM models | Trial and error, evenings | No choice | Tested against your documents by us |
| Hardware | Whatever is spare | None | Specified for the team and rented to you |
| Reads your document library | If you build it | Only what is pasted in | Document spaces with citations |
| Model upgrades and updates | You, when you remember | Automatic | Us, as part of support |
| When it breaks | You | Their status page | Restored from backup by us |
Chosen for Practice Paperwork, Kept Away From the Clinical Record
GP practice AI conversations usually start clinical — triage, coding, note-taking — and those belong inside the clinical system, under its own governance, with a model chosen by someone else. A local LLM in the surgery is for the other half of the practice’s life: the policies and procedures, the complaint responses inside NHS timescales, the PCN and contract reporting, the patient leaflets, the staff handbook, the CQC evidence. That is what the model is chosen for, and it is deliberately not connected to anything clinical.
Those documents point at open-weight models that write careful, plain English and reliably find the right passage in a folder of policies — not the largest model available. A practice’s administrative document set is modest, so the machine is modest: one unit in the practice office, specified for the number of staff who will use it. We shortlist candidates on a call with the practice manager, install the machine, import the policies folder and templates, and test the shortlist on them before settling.
Around the model sit the tools the office actually uses: a private chat assistant for drafting, document spaces that answer “where is our chaperone policy and when was it reviewed?” with the page cited, and a custom assistant that assembles the quarterly PCN report from the practices’ submissions. Sign-in is the Microsoft 365 or Google Workspace account staff already have; nothing leaves the surgery.
Model upgrades are made with the practice manager as part of support, so the drafts the office relies on do not change without warning, and the DSPT entry for this tool stays short: processed on a machine the practice owns, at the surgery, with no third-party AI processor. We would rather the DSPT lead or Caldicott Guardian was on the first call.
The Model Is the Engine. This Is the Car.
A bare model is a demo. GP practices need the machine, the tools around the model, the sign-in and someone to maintain it.
A model matched to the work
An open-weight local LLM chosen and tested against your own documents, on a machine specified to run it well for your team size.
Document spaces around it
The model on its own answers from what you paste in. Spaces let it search, summarise and compare across hundreds of your files, citing the page each answer came from.
Chat and assistants on top
A private chat assistant for the team and custom assistants for the recurring jobs, all running on the same machine as the model.
| Document | What the practice asks for | What stays where |
|---|---|---|
| Policies and procedures | Find it, check the review date, cite the page | On the machine, in the surgery |
| Complaint files | A draft response from the file and your complaints policy | On the machine, in the surgery |
| PCN and contract reporting | The quarterly report assembled from submissions | On the machine, in the surgery |
| Patient letters and leaflets | A draft in the practice’s wording | On the machine, in the surgery |
| National guidance and CQC evidence | A summary against what the practice already does | On the machine, in the surgery |
| Clinical records | Not used — stays in the clinical system | Your clinical system |
From Practice Manager’s Call to a Model in the Office
Weeks, not months. Most practices start with the policies folder or the complaints process; PCNs usually start with one practice.
A call with the practice manager
List size, PCN role, how many staff, which paperwork goes first. We specify the machine from that and walk through the data flow with your DSPT lead.
Install and import
The machine goes on the practice network. Sign-in connects to your Microsoft 365 or Google Workspace. Policies, templates and correspondence are imported into spaces.
Train the office, then support
We train the practice manager, reception and admin team on what it does and what it is not for, then keep the software and models current.
Where Local AI Is the Wrong Answer
We would rather lose the enquiry than the trust. Three things we tell every prospect before they sign anything.
It is not a frontier model
The largest cloud models are still ahead of any local LLM on hard, novel reasoning. If your work needs that, a local model is the wrong tool and we will say so. For summarising, drafting and answering questions about your own documents, most offices are happy with it.
It is slower than the big cloud models
Open-weight models on a single machine are capable for summarising, drafting and answering questions about your own documents. For frontier reasoning on hard, novel problems, the largest cloud models are still ahead. That is the trade.
It is a weeks-long install, not a sign-up
A cloud agent is live in days. Local AI needs the machine specified, delivered, installed on your network and your documents imported. Weeks, not months — but not tomorrow.
We Run Our Own
Chosen against your files
Model selection is tested on a sample of your own documents, not a public leaderboard.
Sized with the model
The machine and the model are specified together. A model the hardware cannot run well is the commonest DIY mistake.
Upgrades made on purpose
Model upgrades are part of support, so someone is deciding when the answers your team relies on are allowed to change.
UK data protection built in
No third-party AI processor and no restricted transfer for the AI step. UK GDPR, the Data Protection Act 2018 and the ICO as regulator, with a data processing agreement for the support access you grant us.
Which Page Answers Your Practice’s Question
| If your question is… | The short answer | Read more |
|---|---|---|
| How is the model chosen in general? | Tested against your documents, not a leaderboard | Local LLM |
| We want the Local AI overview for GP practices | The head page for surgeries | Local AI for GP practices |
| What exactly is installed in the surgery? | One machine in the office, supported | On-Premises AI for gp practices |
| What does our DSPT lead need? | No processor, no transfer, for the AI step | GDPR Compliant AI for gp practices |
| The 8am phone queue is the real problem | A hosted agent, live in days | AI Receptionist |
| We are a dental practice, not a GP | A model in the practice office, managed | Local LLM for dental practices |
| Why on-premises at all? | The case for Local AI, in full | Local AI product page |
Local LLMs for GP Practices: Common Questions
What is a local LLM?
A large language model — the kind of model behind chat assistants — running on hardware you control rather than accessed through a provider’s service. Your prompts, uploaded documents and chat history stay on that machine in the surgery.
Which local LLM models do you install?
It depends on the job. Drafting and summarising, answering questions across a document library, and structured extraction each favour different open-weight models, and the machine has to fit the model. We shortlist and test candidates against a sample of your own documents during setup.
Does the model ever see the clinical system?
No. It is not connected to the clinical system and does not read the clinical record. It works on the administrative documents imported into spaces on the machine — policies, correspondence, reports, leaflets. Clinical questions go to a clinician, not the model.
Who decides when the model is upgraded?
You do, with us. New model versions arrive regularly and a careless upgrade changes how drafts read. Upgrades are part of support and are made with the practice manager, on a date the practice chooses.
Does it connect to our clinical system?
No, and it should not. The clinical record stays in your clinical system. It works on the documents around the practice — policies, correspondence, reports, leaflets — which are imported into spaces on the machine.
How does it fit with the Data Security and Protection Toolkit?
The DSPT asks you to know where data is processed and by whom. With a machine in the surgery the answer is: here, by nobody else. There is no third-party AI processor and no transfer for the work it does. Bring your DSPT lead or Caldicott Guardian to the call.
How much does Local AI cost?
£500 per month for the software and the hardware rental. The dedicated machine is rented to your business, not sold: you never buy the hardware. It is installed in your building and runs the private chat, document spaces and assistants. Local AI is for business customers only.
Let the Model Be Our Problem
Tell us your list size and which paperwork takes the practice manager longest. One short call to choose the model and size the machine, with your DSPT lead welcome on the line.
Prefer email? sghaith@businessaiagents.co.uk